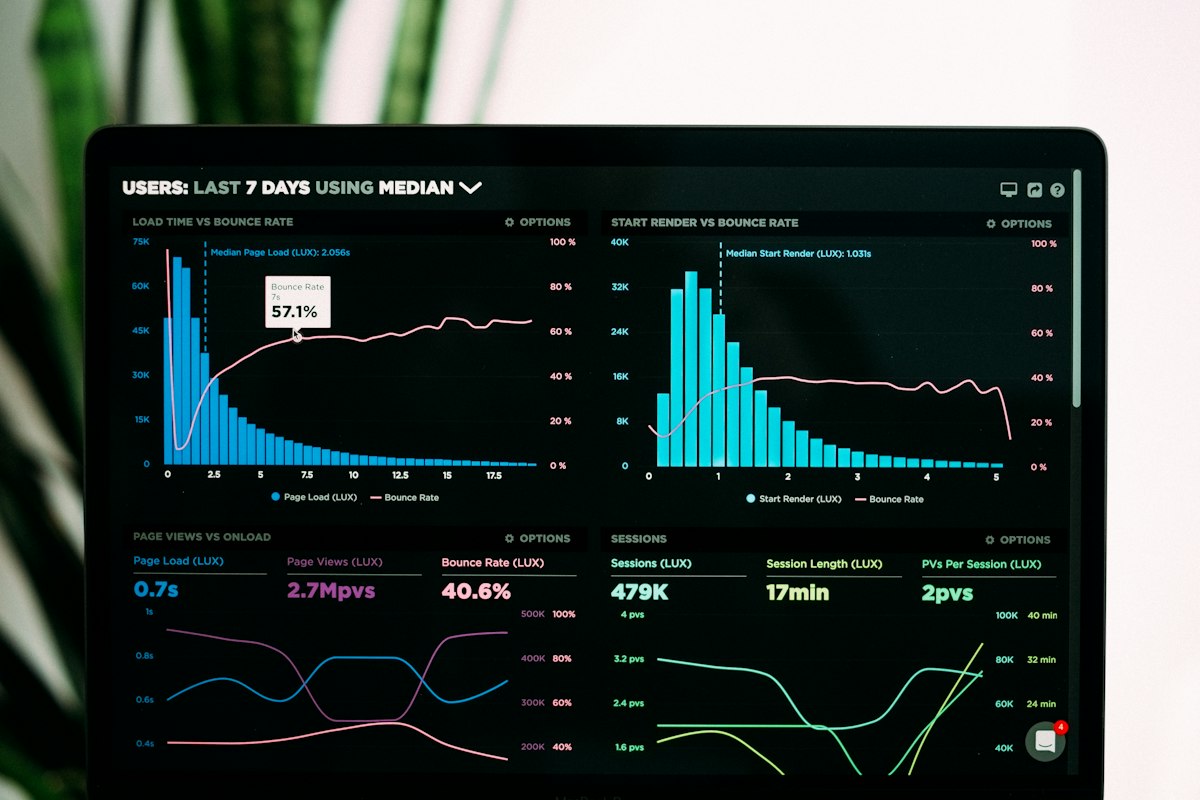
In the competitive landscape of modern marketing, understanding the impact of advertising spend is important. For businesses with physical locations, a common question is: Are digital ads associated with more visits to our doors? Foot Traffic Attribution is one way to evaluate that question for permitted, non-health retail and commercial campaigns. It compares advertising exposure and store-visit signals using a defined measurement methodology. The resulting analysis can inform campaign evaluation, but it is not a direct measure of an individual’s intent, a sale, or a guaranteed return on investment.
Understanding the Mechanics: How Foot Traffic Attribution Works
At its core, foot traffic attribution can use location intelligence technology, including geofencing, for permitted non-health commercial locations. A simplified measurement workflow may include:
- Location definition: A campaign defines relevant non-health retail or commercial locations and a measurement period. Healthcare facilities, clinical-care areas, pharmacies, dental offices, patient parking, and similar health-service locations are not appropriate audience sources, retargeting triggers, or conversion zones.
- Ad-delivery measurement: A provider may record campaign delivery signals and measurement events under its applicable program and product terms.
- Store-visit measurement: A provider may evaluate whether an advertising identifier, which can be pseudonymous and potentially linkable, is observed at a permitted store location within a pre-defined attribution window. The methodology, confidence thresholds, and limitations should be documented before results are interpreted.
- Reporting: Results may be presented in aggregate to compare campaign groups, creatives, or locations. Aggregate presentation alone does not determine the legal status of the underlying exposure, device, location, or matching data.
This approach can supplement online metrics such as clicks and impressions for ordinary commercial campaigns. It should be treated as one input to evaluation rather than conclusive proof that advertising caused a specific person to visit or purchase.
Key Metrics and Data Points for Measurement
A measurement plan can define the following metrics for permitted non-health campaigns:
- Visit Rate: The reported percentage of measured ad-exposed identifiers associated with a later visit to a permitted physical location during the selected window.
- Incremental Visits: An estimate intended to compare an exposed group with a control group. It depends on the study design and assumptions and should not be presented as certain causation.
- Visit Lift: The reported difference in visit rates between defined groups, subject to the measurement methodology and its limitations.
- Creative and channel comparisons: Aggregate comparisons that can help a team decide which messages or channels warrant additional testing.
- Timing and location patterns: Aggregate patterns for permitted locations that may inform future measurement hypotheses without profiling people based on health visits or conditions.
Teams should document the metric definitions, attribution window, control methodology, and known limitations so stakeholders can interpret results appropriately.
Examples of Permitted Commercial Uses
Retail
A clothing retailer can evaluate an offer campaign at its own non-health retail locations using a pre-defined methodology and compare aggregate results across markets or creative versions.
Automotive
An automotive dealership group can evaluate advertising for its own lots and use the resulting aggregate reporting to decide whether to test different creative, channels, or local-market approaches. This is distinct from using healthcare-location visits or health-related signals for advertising.
Restaurants & Quick Service (QSR)
A restaurant chain can assess a lunchtime offer at its restaurants, then use aggregate findings to guide further tests in comparable markets.
Campaign Implications: Using Results Carefully
- Budget evaluation: Use a documented measurement plan to compare channels, creatives, or markets before making allocation decisions.
- Creative testing: Test messages and calls to action using aggregate outcomes and other relevant business measures.
- Location planning: Focus on permitted commercial locations and broad, non-health geographic context.
- Reporting: Explain the attribution method, assumptions, and limits alongside reported results rather than treating reported visits as confirmed sales or individual intent.
Healthcare-Specific Limits
Healthcare marketing should not use visits to hospitals, emergency rooms, urgent-care centers, pharmacies, dental or orthodontic offices, medical or dermatology practices, medspas, plastic-surgery practices, surgical centers, weight-management clinics, patient parking, or clinical-care areas as advertising audience sources, retargeting triggers, inferred condition or procedure signals, or conversion zones. It also should not use patient, clinical, appointment, or healthcare CRM inputs; health-derived household or cross-device expansion; or clinical-intake linkage for advertising measurement or activation.
For healthcare communications, consider broad geographic, contextual, community, professional-event, education, referral-awareness, or employer-owned outreach that does not identify people through health visits or infer their health. Any proposed healthcare campaign requires campaign-specific review of the data, vendor roles, permissions, state law, and platform rules. Reporting access and permitted uses should be defined for the specific campaign. Mediavision2020 does not certify legal compliance.
Challenges and Best Practices for Accurate Attribution
Foot traffic attribution involves methodological and data-governance limitations. A practical approach is to:
- Document the methodology: Review the provider’s definitions, confidence thresholds, data sources, and limitations before relying on a result.
- Define attribution windows: Establish a reasonable timeframe between ad delivery and a reported visit, and disclose that choice when presenting results.
- Use appropriately designed controls: Where suitable, use control groups and describe the study design rather than assuming all reported visits are incremental.
- Set data boundaries: Do not link health-derived location, visit, patient, clinical, appointment, or intake data to advertising or attribution. Aggregate reporting does not remove the need to assess the source data and permitted uses.
- Seek campaign-specific review: Evaluate the relevant data, vendor roles, permissions, state law, and platform rules for the proposed campaign; no general statement on this page establishes compliance.
Conclusion
For permitted non-health commercial campaigns, foot traffic attribution can provide an additional, method-dependent view of how advertising and physical-location outcomes may relate. Define the methodology in advance, interpret aggregate findings with appropriate caution, and keep healthcare marketing away from health-provider-visit audiences, patient or clinical inputs, and health-linked measurement.
Contact our team at Mediavision2020 for a free consultation here.